
 Individuals


 Allied Health

 Medical Practitioners


Hypermobile Ehlers-Danlos Syndrome (hEDS) and Hypermobility Spectrum Disorder (HSD) are often associated with flexible or “double-jointed” joints. However, both are increasingly recognised as complex, multisystem connective tissue disorders that can affect far more than simply your muscles and joints [1, 2, 3].
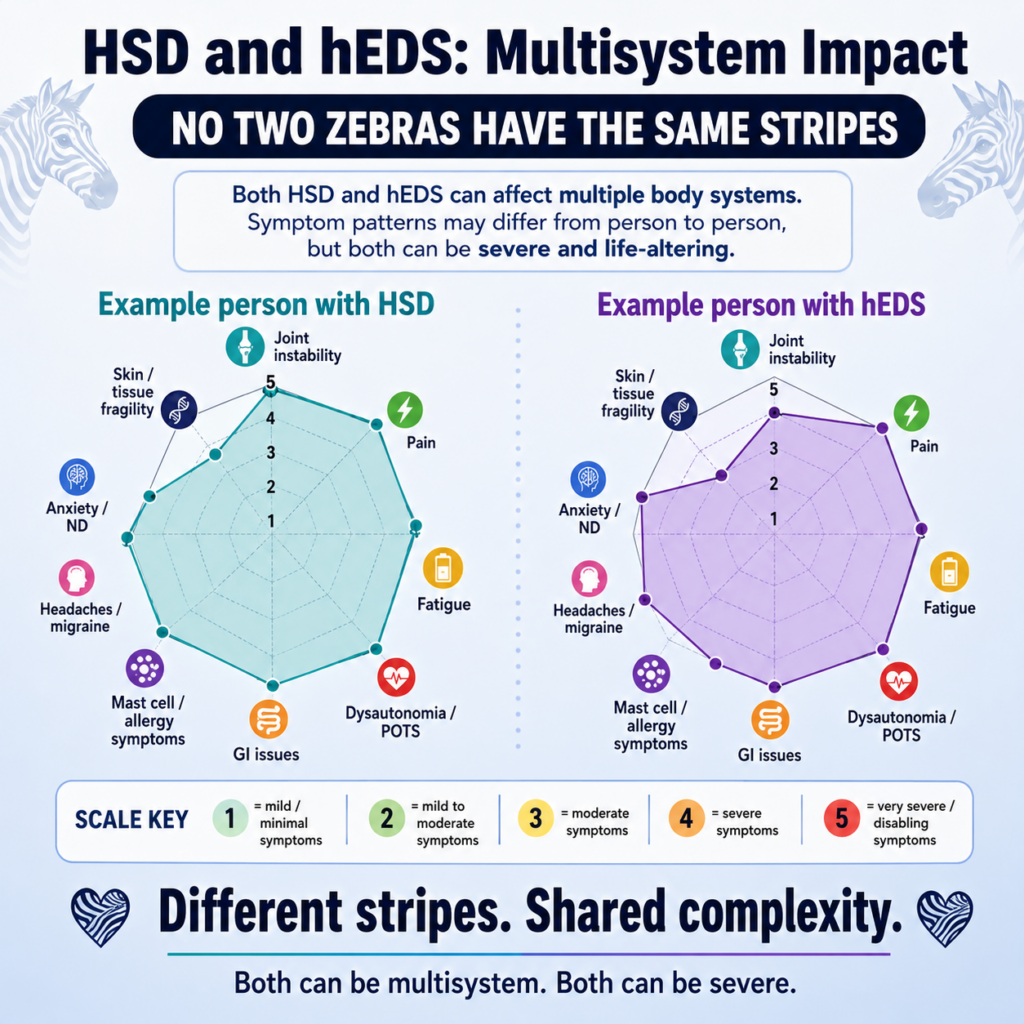
Having a diagnosis of HSD can be just as life-impacting and debilitating as hEDS. People with symptomatic hypermobility, hEDS and HSD often experience multiple comorbidities or co-occurring health conditions. These symptoms and conditions can present as: significant pain across the muscles, joints and other body parts; automatic body function impact (fatigue, heart racing, temperature regulation, dizziness, etc), anxiety, gut and digestion issues, conditions usually relating to the nervous or immune systems, neurodivergence and mental health problems. These co-occurring conditions/symptoms are often known as additional “Invisible Illnesses”, and for many, these conditions have a greater impact on daily life than joint instability and pain alone [4, 5, 6, 7,8].
This article explores why these conditions commonly occur together, helping move the discussion beyond “bendy joints” and towards a more accurate understanding of hEDS and HSD as interconnected, whole-body conditions.
Are you Hypermobile, or think you may have HSD or hEDS?
Take our 15-min evidence-based online test to find out if you might benefit from professional support.
Health conditions, comorbidities and co-occurring conditions: What’s the difference?
- A health condition is any disease, disorder, injury, syndrome, or ongoing physical or mental health issue that affects a person’s health, wellbeing, or daily functioning.
- A comorbidity is an additional health condition or health issue that exists alongside a primary diagnosis. The term “comorbidity” does not mean automatically that one condition caused another. It simply means that two or more conditions are present in the same person.
While the term “comorbidity” has traditionally been used in medicine, many clinicians and researchers discussing hEDS and HSD now prefer “co-occurring conditions.” This term better reflects how complex and interconnected these presentations can be.
It also avoids suggesting that one condition is secondary, less important, or separate from the wider clinical picture. For example, treating joint instability, chronic pain, gastrointestinal dysfunction, autonomic symptoms, fatigue, and migraine as unrelated problems may mean the broader pattern is missed.
The distinction is therefore important. A comorbidity may be recorded as an additional diagnosis, while “co-occurring condition” recognises that several conditions may be present and interact, even when their exact relationship is not yet fully understood.
Why so many “Invisible Illnesses” occur together in hEDS/HSD – New research
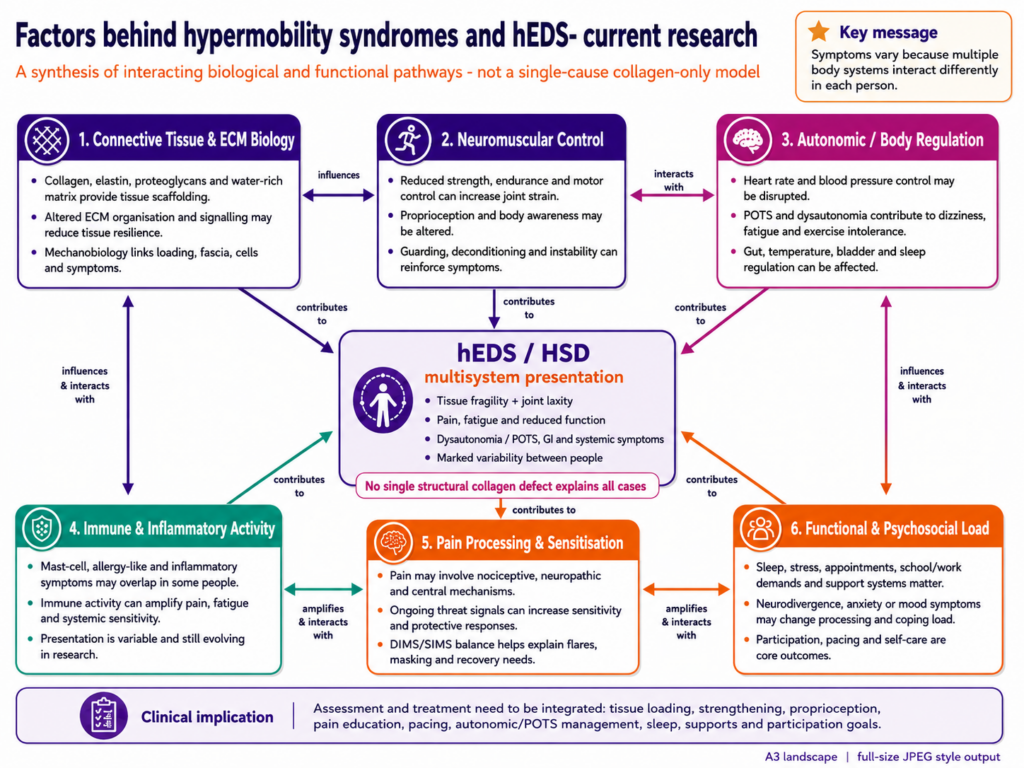
Connective tissue was originally thought to be the main reason hEDS and HSD affect so many parts of the body. It gives the body strength, flexibility, support and cushioning. Connective tissue is found not only in joints and ligaments, but also in and around muscles, fascia, tendons, skin, blood vessels, nerves, the digestive system and organs such as the heart, lungs and bladder. Because it is found throughout the body, changes in connective tissue and the surrounding support network may contribute to symptoms in several body systems [2, 11, 12, 13].
Current research suggests that hEDS and HSD are probably caused by several interacting factors, rather than one problem with collagen or connective tissues. Changes in the body’s support network, fascia, cell communication, muscle control, automatic body functions, immune activity, pain processing and nerve function may all play a part [4, 11, 12, 13, 14, 15, 16].
This helps explain why a person with hEDS or HSD may experience different combinations and severity of joint instability, pain, fatigue, dizziness, poor sleep, digestive symptoms, body awareness, anxiety, autonomic function and difficulty with daily activities, rather than only joint hypermobility.
The precise causes and relationships between these mechanisms are still being investigated.
Are you Hypermobile, or think you may have HSD or hEDS?
Take our 15-min evidence-based online test to find out if you might benefit from professional support.
The most common co-occurring conditions / “Invisible Illnesses” in the Symptomatic Hypermobility Syndromes and hEDS
Chronic widespread pain
Chronic pain is one of the most common and disabling features of hEDS and HSD. It may result from joint instability, muscle overuse, nerve irritation, or central pain sensitisation, where the nervous system becomes more sensitive and pain persists or spreads beyond the original injury [17, 18, 19]. Pain often fluctuates and may not be clearly explained by imaging, which can delay diagnosis.
Joint instability, subluxations and dislocations
Subluxations and dislocations are common in both hEDS and HSD. A subluxation is a partial dislocation, while a full dislocation occurs when the joint surfaces lose contact and move out of alignment. This ongoing joint instability can also cause muscle guarding, nerve irritation, fear of movement, and ongoing pain [5, 20, 21].
Postural Orthostatic Tachycardia Syndrome (POTS) and dysautonomia
Autonomic dysfunction is common in hEDS and HSD. POTS is only one presentation in dysautonomia or autonomic dysfunction and can cause dizziness, palpitations, fatigue, brain fog, nausea, and fainting when standing. Lax connective tissue in blood vessels may contribute to blood pooling and poor circulation, triggering these symptoms [22, 23, 24].
Fatigue and Chronic Fatigue Syndrome (CFS)
Fatigue in hEDS and HSD is often persistent and can be severe or out of proportion to activity. It may be linked to pain, poor sleep, autonomic dysfunction, immune activation, gut issues, sensory system overload and the extra effort needed to stabilise hypermobile joints [19, 24].
Gastrointestinal disorders
Common digestive symptoms include reflux, bloating, constipation, diarrhoea, nausea, early fullness, and abdominal pain. Irritable bowel syndrome, gut dysmotility, and functional gastrointestinal disorders are also frequently reported [25]. Connective tissue differences-hypermobility within the gut and autonomic dysfunction have been found to affect gut movement, sensitivity, and digestion [14, 25, 26, 27].

Headache and migraine disorders
Migraine and chronic headache are much more common in people with hEDS and HSD than in the general population. Possible contributors include cervical instability, muscle tension, autonomic dysfunction, and altered pain processing [28, 29, 30].
Anxiety disorders
Anxiety is more common in hEDS and HSD, but this does not mean physical symptoms are psychological. Possible shared mechanisms include autonomic nervous system and actual nervous system differences and increased interoceptive awareness, or sensitivity to internal body signals [31, 32, 33]. Anxiety may also result from unpredictable symptoms, functional limitations, ongoing invalidation and long diagnostic delays.
Depression
Depression is reported more often in people with hEDS and HSD, particularly when pain, fatigue, and functional limitations are poorly managed. Social isolation, medical invalidation, and repeated treatment failures can also affect mental health [34].
Sleep disorders
Common sleep problems include insomnia, non-restorative sleep, restless legs, and sleep-disordered breathing. Pain, autonomic symptoms, and anxiety can disrupt sleep, while poor sleep can worsen fatigue and pain sensitivity [6] .
Neurodivergent conditions, including ADHD and autism
Higher rates of ADHD and autism have been reported in people with hEDS and HSD. Research is ongoing, including into possible shared neurodevelopmental and connective tissue pathways [9, 31, 32, 35, 36].
Mast cell activation disorders
Mast cell activation symptoms, including flushing, itching, hives, gastrointestinal upset, bloating, headaches, and medication sensitivities, are frequently reported in hEDS and HSD. Research is still developing, but mast cell activation and immune dysregulation appear to overlap with connective tissue disorders in some people [37, 38, 39].
Temporomandibular joint disorders
TMJ disorders can cause jaw pain, clicking, locking, headaches, and facial pain. They may result from jaw hypermobility and muscle overuse and can affect eating, speaking, and quality of life [9].
Pelvic floor dysfunction and gynaecological conditions
Pelvic floor dysfunction can affect people of all genders and may cause bladder or bowel problems, prolapse, pelvic pain, and sexual pain. Reduced connective tissue support, pain, and muscle guarding may all contribute [4, 6, 40].
Small fibre neuropathy
Small fibre neuropathy affects nerves involved in pain and autonomic function. Symptoms can include burning pain, tingling, temperature sensitivity, altered sweating, and other autonomic problems. Research suggests it may be under-recognised in hEDS and HSD [4].
Cardiovascular differences
Most people with hEDS or HSD do not have life-threatening heart conditions. However, mild valve changes, orthostatic intolerance, and circulation problems are more common and may worsen fatigue, exercise intolerance, and autonomic symptoms [6].
Why this matters for diagnosis and care
Because hEDS and HSD can affect many body systems, people often see multiple health professionals before receiving an accurate diagnosis. Their symptoms may be treated separately, without anyone recognising the broader pattern.
Some people are told that their symptoms are unrelated, caused by stress, or “just anxiety.” This can contribute to delayed diagnosis, repeated investigations, medical traumatisation invalidation, and treatments that do not address the full clinical picture [41, 42].
Recognising common co-occurring conditions can help to:
- Validate people’s experiences
- Reduce diagnostic delays and improve treatment planning
- Encourage multidisciplinary care
- Identify patterns across different body systems
- Shift the focus from isolated symptoms to whole-person management
For people living with hEDS and HSD
hEDS and HSD are not simply conditions of flexible or unstable joints. They are complex, interconnected conditions that can affect the body as a whole. Recognising common co-occurring conditions can help people better understand their symptoms and feel less alone. It may also help explain why concerns such as pain, fatigue, digestive problems, dizziness, migraine, sleep difficulties, and other symptoms can occur together.
HSD can be just as disruptive as hEDS, even when a person does not meet the full diagnostic criteria for hEDS. Every presentation is different, but symptoms should not be dismissed simply because they affect several body systems or cannot be explained by one diagnosis.
Understanding the wider pattern is an important step towards more coordinated, compassionate, and effective care.
Are you Hypermobile, or think you may have HSD or hEDS?
Take our 15-min evidence-based online test to find out if you might benefit from professional support.
For GPs and Allied Health Professionals
Hypermobile Ehlers-Danlos syndrome and Hypermobility Spectrum Disorders are multisystem connective tissue disorders, not isolated musculoskeletal conditions. Many patients experience significant multimorbidity involving the autonomic, gastrointestinal, neurological, immune, psychological, and musculoskeletal systems.
Why this matters in clinical practice
Patients may present with fragmented symptoms and consult several health professionals before the wider pattern is recognised. Diagnostic delays are common, and physical symptoms may be incorrectly attributed to anxiety or functional illness.
Clinicians should consider hEDS or HSD when a patient presents with:
- Long-standing pain alongside hypermobility
- Joint instability or recurrent subluxations
- Multiple unexplained symptoms across different body systems
- Poor responses to standard single-system treatments
- Symptoms beginning in childhood or adolescence
- A family history of hypermobility or related conditions
Common co-occurring concerns that may require screening include:
- Chronic widespread pain
- Joint instability and poor injury recovery
- Persistent fatigue and non-restorative sleep
- Migraine and chronic headache
- Anxiety and depression, which may be co-occurring not the main cause
- Dysautonomia or POTS
- Central sensitisation of pain, fibromyalgia or FND
- Gastrointestinal disorders
- Mast cell activation symptoms
- Pelvic floor dysfunction
- Temporomandibular joint disorders
- Neurodivergent traits, including ADHD and Autism
- Small fibre neuropathy
Principles of care
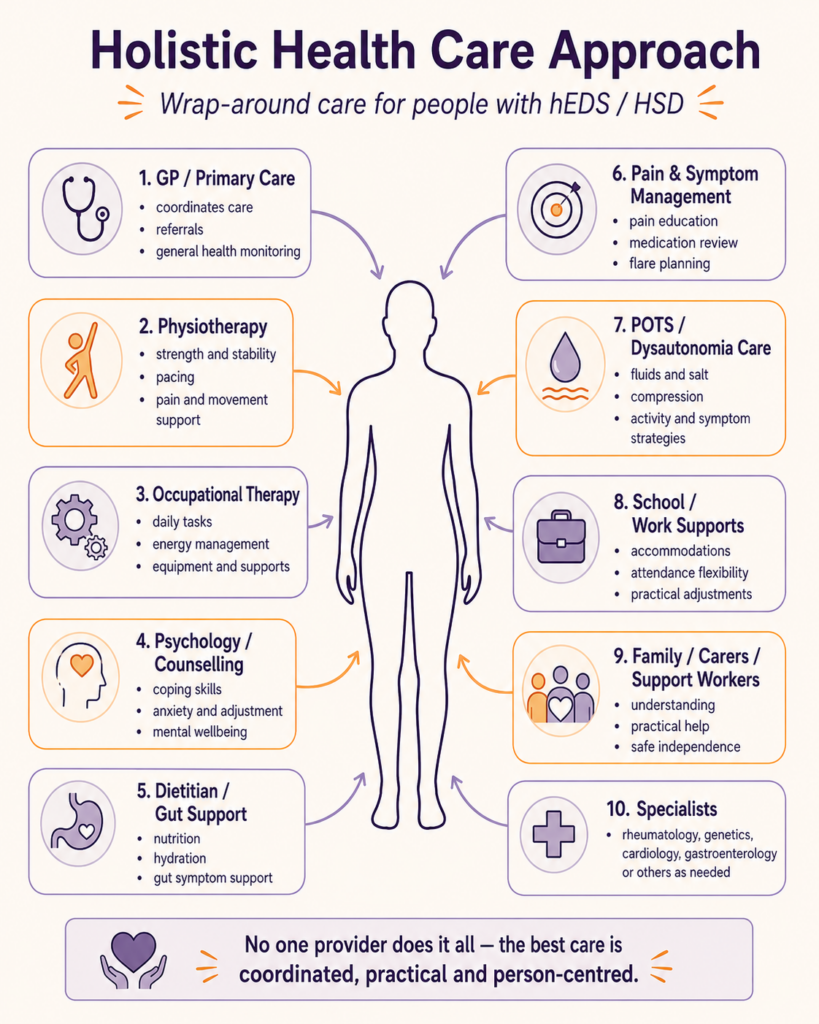
Management should reflect the multisystem nature of hEDS and HSD. Depending on the patient’s needs, this may involve support from general practitioners, physiotherapists, occupational therapists, psychologists, cardiologists, gastroenterologists, and other relevant health professionals [43, 44, 45].
Important principles include:
- Validating the patient’s symptoms and provide hope (treatment and management options are available)
- Recognising multisystem involvement as part of the clinical picture
- Screening proactively rather than reactively
- Looking for patterns and clusters of symptoms
- Focusing on function, pacing, and quality of life
- Coordinating care across health disciplines where needed
Symptomatic Hypermobility, hEDS and HSD are conditions of complexity, not hypochondria or exaggeration. Treating each symptom as an unrelated problem can lead to missed diagnoses, delayed care, and poorer outcomes.
Recognising predictable patterns of co-occurring conditions can improve diagnostic confidence, strengthen patient trust, and support safer and more effective management.
A whole-body condition requires whole-person care.

Are you a health professional looking to learn more?
We offer training and professional development to help health professionals better understand hypermobility, HSD and hEDS.
Contact Us to discuss training opportunities for you, your team or your organisation.
Are you Hypermobile, or think you may have HSD or hEDS?
Take our 15-min evidence-based online test to find out if you might benefit from professional support.
References
- Castori, M., Generalized joint hypermobility and pain: When generalized joint hypermobility changes from an asset to a health concern. 2023. p. 23-28.
- Malfait, F., et al., The 2017 international classification of the Ehlers–Danlos syndromes. American journal of medical genetics. Part C, Seminars in medical genetics, 2017. 175(1): p. 8-26.
- Gensemer, C., et al., Hypermobile Ehlers‐Danlos syndromes: Complex phenotypes, challenging diagnoses, and poorly understood causes. Developmental dynamics, 2021. 250(3): p. 318-344.
- Petrucci, T., et al., Phenotypic Clusters and Multimorbidity in Hypermobile Ehlers-Danlos Syndrome. Mayo Clinic proceedings. Innovations, quality & outcomes, 2024. 8(3): p. 253-262.
- Eichinger, J.K., et al., Orthopaedic Manifestations in Hypermobile Ehlers-Danlos Syndrome. Journal of bone and joint surgery. American volume, 2025. 107(16): p. 1848-1856.
- Victoria Daylor, M.G., Amy Weintraub, Rebecca Byrd, Taylor Petrucci, Matthew Huff, Kathryn Byerly, Roman Fenner, Sydney Severance, Charlotte Griggs, Amol Sharma, Paldeep Atwal, Steven A. Kautz, Steven Shapiro, Kimberly Youkhana, Mark Lavallee, Allison Wilkerson, Michelle Nichols, Alan Snyder, Josef Eichinger, Sunil Patel, Anne Maitland, Cortney Gensemer, View ORCID ProfileRussell A. Norris, Defining the Clinical Complexity of hEDS and HSD: A Global Survey of Diagnostic Challenge, Comorbidities, and Unmet Needs. 2024.
- Halverson, C.M.E., et al., Comorbidity, misdiagnoses, and the diagnostic odyssey in patients with hypermobile Ehlers-Danlos syndrome. Genetics in Medicine Open, 2023. 1(1): p. 100812.
- Hakim, A., et al., Chronic fatigue in Ehlers–Danlos syndrome—Hypermobile type. American journal of medical genetics. Part C, Seminars in medical genetics, 2017. 175(1): p. 175-180.
- Daylor, V., et al., Defining the Clinical Complexity of hEDS and HSD: A Global Survey of Diagnostic Challenge, Comorbidities, and Unmet Needs. 2025.
- Wachs, S. and C. Papendorp, Prevalence of various comorbidities in a cohort of individuals with hypermobile Ehlers-Danlos syndrome. Journal of rare diseases (Berlin, Germany), 2026. 5(1): p. 7-7.
- Malek, S. and D.V. Köster, The Role of Cell Adhesion and Cytoskeleton Dynamics in the Pathogenesis of the Ehlers-Danlos Syndromes and Hypermobility Spectrum Disorders. Frontiers in cell and developmental biology, 2021. 9: p. 649082.
- Ritelli, M., et al., RNA-Seq of Dermal Fibroblasts from Patients with Hypermobile Ehlers–Danlos Syndrome and Hypermobility Spectrum Disorders Supports Their Categorization as a Single Entity with Involvement of Extracellular Matrix Degrading and Proinflammatory Pathomechanisms. Cells (Basel, Switzerland), 2022. 11(24): p. 4040.
- Wang, T.J., et al., Fascial Pathophysiology in Hypermobility Spectrum Disorders and Hypermobile Ehlers–Danlos Syndrome: A Review of Emerging Evidence, in Int J Mol Sci. 2025, MDPI AG: Switzerland. p. 5587.
- Pasricha, P.J., et al., Joint Hypermobility, Autonomic Dysfunction, Gastrointestinal Dysfunction, and Autoimmune Markers: Clinical Associations and Response to Intravenous Immunoglobulin Therapy. The American journal of gastroenterology, 2024. 119(11): p. 2298-2306.
- Fernandez, A., et al., Small fiber neuropathy in hypermobile Ehlers Danlos syndrome/hypermobility spectrum disorder. Journal of internal medicine, 2022. 292(6): p. 957-960.
- Igharo, D., et al., Skin biopsy reveals generalized small fibre neuropathy in hypermobile Ehlers–Danlos syndromes. European journal of neurology, 2023. 30(3): p. 719-728.
- Börsch, N., et al., Treating pain in patients with Ehlers–Danlos syndrome: Multidisciplinary management of a multisystemic disease. Schmerz (Berlin, Germany), 2024. 38(1): p. 12-18.
- Chopra, P., Tinkle Brad, Claude Hamonet, Isabelle Brock, Anne Gompel, Antonio Bulbena, And Clair Francomano, Pain management in the Ehlers–Danlos syndromes. American journal of medical genetics. Part C, Seminars in medical genetics, 2017.
- Castori, M., et al., Management of pain and fatigue in the joint hypermobility syndrome (a.k.a. Ehlers-Danlos syndrome, hypermobility type): Principles and proposal for a multidisciplinary approach. American journal of medical genetics. Part A, 2012. 158A(8): p. 2055-2070.
- Russek, L.N., P. Stott, and J. Simmonds, Recognizing and Effectively Managing Hypermobility-Related Conditions. Physical therapy, 2019. 99(9): p. 1189-1200.
- Simmonds, J.V., Masterclass: Hypermobility and hypermobility related disorders. Musculoskeletal science & practice, 2022. 57: p. 102465-102465.
- POTS., S.U.t. POTS Symptoms. 2025 [cited 2025 1st October]; Available from: https://www.standinguptopots.org/potssymptoms?utm_source=chatgpt.com.
- Novak, P., et al., Hypermobile Ehlers-Danlos Syndrome: Cerebrovascular, Autonomic and Neuropathic Features. American journal of medicine open, 2025. 14: p. 100111-100111.
- Collins Hutchinson, M.L., et al., Autonomic symptom burden, comorbidities and quality of life in women with Hypermobility Spectrum Disorders and hypermobile Ehlers-Danlos syndrome. Autonomic neuroscience, 2025. 262: p. 103356-103356.
- Dobb, D.E. and D.C. Wells, Management of gastrointestinal and nutritional issues in patients with hypermobile Ehlers-Danlos syndrome. Clinical nutrition ESPEN, 2024. 61: p. 483-483.
- Eckardt, A.J., T. Wehrmann, and C.C. Brueck, Esophageal Striae as a Possible Gastrointestinal Manifestation of Hypermobile Ehlers-Danlos Syndrome. ACG case reports journal, 2024. 11(6): p. e01393.
- Alomari, M., et al., Prevalence and Predictors of Gastrointestinal Dysmotility in Patients with Hypermobile Ehlers-Danlos Syndrome: A Tertiary Care Center Experience. Curēus, 2020. 12(4): p. e7881-e7881.
- Russek, N.L., et al., Presentation and physical therapy management of upper cervical instability in patients with symptomatic generalized joint hypermobility: International expert consensus recommendations. Frontiers in Medicine, 2023. 9.
- Nicholson, L.L., et al., Is there a relationship between sagittal cervical spine mobility and generalised joint hypermobility? A cross-sectional study of 1000 healthy Australians. Physiotherapy, 2021. 112(NA): p. 150-157.
- Mehta, D., et al., Headache disorders in patients with Ehlers-Danlos syndromes and hypermobility spectrum disorders. Frontiers in neurology, 2024. 15: p. 1460352.
- Eccles, J.A., et al., Variant connective tissue (joint hypermobility) and its relevance to depression and anxiety in adolescents: a cohort-based case–control study. BMJ open, 2022. 12(12): p. e066130-e066130.
- Bulbena, A., et al., Joint Hypermobility, Anxiety and Psychosomatics: Two and a Half Decades of Progress Toward a New Phenotype. 2015, S. Karger AG: Basel, Switzerland. p. 143-157.
- Kampoureli, C.N., et al., Neural processes linking joint hypermobility and anxiety: key roles for the amygdala and insular cortex. British journal of psychiatry, 2025: p. 1-7.
- Berglund, B., et al., Self-reported quality of life, anxiety and depression in individuals with Ehlers-Danlos syndrome (EDS): a questionnaire study. BMC Musculoskeletal Disorders, 2015. 16(1).
- Guinchat, V., et al., Editorial: Neurodevelopmental, neuropsychiatric and psychosocial correlates of joint hypermobility and related disorders. Frontiers in psychiatry, 2022. 13: p. 1109515-1109515.
- Bulbena‐Cabré, A. and A. Bulbena, Corrigendum: Psychiatric and psychological aspects in the Ehlers–Danlos syndromes. American journal of medical genetics. Part A, 2017. 173(12): p. 3241-3241.
- Farley, M., et al., Prevalence of mast cell activation disorders and hereditary alpha tryptasemia among patients with postural orthostatic tachycardia syndrome and Ehlers-Danlos syndrome: A systematic review. Annals of allergy, asthma, & immunology, 2025. 135(1): p. 97-102.
- Weinstock, L.B., et al., Mast Cell Activation Syndrome: A Primer for the Gastroenterologist. Digestive diseases and sciences, 2021. 66(4): p. 965-982.
- Afrin, L., Some cases of hypermobile Ehlers–Danlos syndrome may be rooted in mast cell activation syndrome. . American Journal of Medical Genetics, 2021. 187: p. 466–472.
- Blagowidow, N., Gynecologic and Obstetric Issues in HSD and EDS., in The Ehlers-Danlos Society-International Global Learning Conference. 2018: Baltimore.
- Halverson, C.M.E., H.L. Penwell, and C.A. Francomano, Clinician-associated traumatization from difficult medical encounters: Results from a qualitative interview study on the Ehlers-Danlos Syndromes. SSM. Qualitative research in health, 2023. 3: p. 100237.
- Trudgian, R. and T. Flood, An exploration of the journey to diagnosis of Ehlers-Danlos Syndrome (EDS) for women living in Australia. PloS one, 2024. 19(7): p. e0307574.
- Hakim Alan, T.L., Hassan Luke, Slater Pauline, Rao Prash, Knight Dacre, Francomano Claire. Keynote Panel: The Importance of Teamwork in Diagnosing & Managing EDS & HSD Patients. in 2025 Global Learning Conference. 2025. Brisbane, Australia.
- Francomano, A.C., et al., Introduction: An overview of the Ehlers-Danlos syndromes and hypermobility spectrum disorders, in The Symptom-Based Handbook for Ehlers-Danlos Syndromes and Hypermobility Spectrum Disorders. 2024. p. 1-17.
- Hakim, A., Hypermobile Ehlers-Danlos Syndrome Synonyms: Ehlers-Danlos Syndrome Hypermobility Type, Ehlers-Danlos Syndrome Type III, hEDS. October 22 ed. GeneReviews®, ed. F.J. Adam MP, Mirzaa GM, et al., . 2024, University of Washington, Seattle: U.S. National Library of Medicine. 16.

















